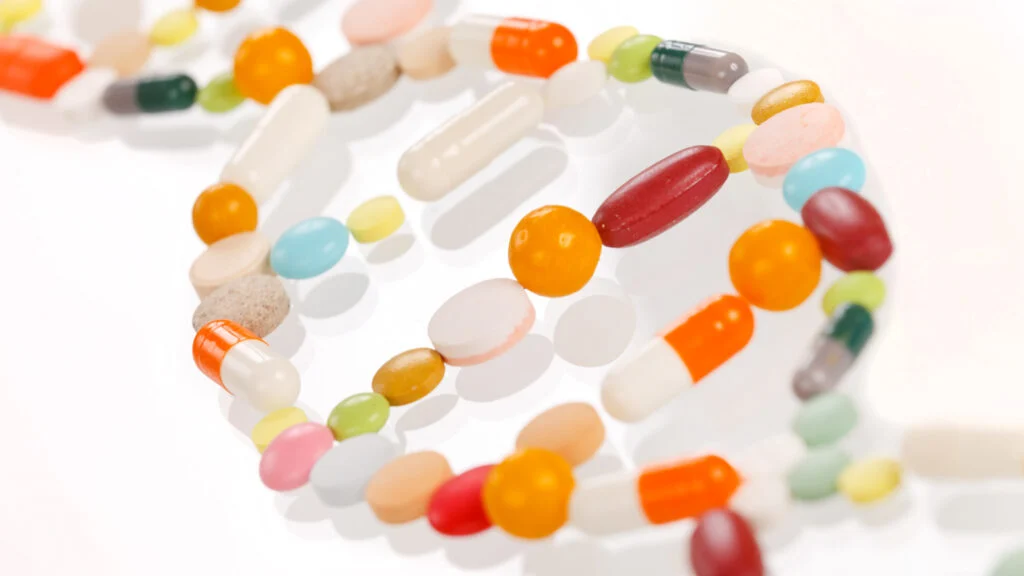
A landmark study of nearly 100,000 Americans has unveiled thousands of previously unidentified genetic variants that dictate how individuals respond to prescription medications, marking a significant leap forward in the field of pharmacogenomics. By leveraging the National Institutes of Health’s (NIH) expansive All of Us Research Program, researchers have successfully addressed a long-standing critique of genetic studies: the historical lack of ancestral diversity in genomic databases. The findings, published Wednesday in Science Translational Medicine, underscore the critical necessity of inclusive research in ensuring that precision medicine benefits all populations equally.
The research highlights that every participant studied carried at least one genetic variant in the 16 core pharmacogenes analyzed, with one in four individuals currently taking a medication directly influenced by these genetic markers. These genes dictate how the body metabolizes everything from common blood thinners like Plavix and cholesterol-lowering statins to complex chemotherapy regimens and selective serotonin reuptake inhibitors (SSRIs).
The Evolution of Pharmacogenomics
Pharmacogenomics—the study of how genes affect a person’s response to drugs—has long promised to replace the "one-size-fits-all" approach to prescribing medication. Historically, however, the genomic data used to build these predictive models were heavily skewed toward populations of European ancestry. This bias often resulted in diagnostic tools and dosage guidelines that were less accurate, or even misleading, for individuals of African, Hispanic, Asian, or Indigenous descent.
The All of Us Research Program was specifically designed to rectify this imbalance, with a goal of enrolling one million participants from a broad spectrum of backgrounds. By tapping into this diverse dataset, the research team, led by experts at the University of Pittsburgh, was able to identify variants that remained invisible in previous large-scale studies, such as the U.K. Biobank. This achievement is not merely academic; it is a clinical imperative. If a patient experiences a severe adverse reaction or finds a drug entirely ineffective, clinicians often have no immediate way to determine if genetics are the culprit. This new data set provides a more robust roadmap for clinicians to tailor treatments, potentially minimizing the trial-and-error cycle that characterizes much of modern medicine.
Chronology and Scientific Context
The journey toward this milestone has been characterized by steady progress punctuated by administrative hurdles.
- 2016: The 21st Century Cures Act is enacted, providing the foundational legislative and funding support for the All of Us Research Program.
- 2018: The program officially launches its national enrollment efforts, aiming for a longitudinal study of unprecedented scale.
- 2023: The program expands its scope to include pediatric participants, recognizing that genetic influences on drug metabolism are as critical in children as they are in adults.
- 2024: The study published in Science Translational Medicine demonstrates the high prevalence of pharmacogenetic variants, providing the most comprehensive evidence to date for the necessity of clinical integration.
- 2025-2027: The program faces a critical budgetary inflection point as the initial funding streams provided by the Cures Act approach expiration.
Analyzing the Clinical Implications
Philip Empey, director of the Center for Clinical Pharmaceutical Sciences at the University of Pittsburgh and the senior author of the study, emphasizes that while the findings are groundbreaking, the path to routine clinical adoption remains obstructed. "If you have a prior experience with a medicine that did not work for you, or had a side effect, we can’t say it’s absolutely because of genetics, but we are appreciating more and more that people are different, and genetics is one reason that may suggest where there may be differences," Empey noted.

The barriers to clinical implementation are manifold. First, genomic sequencing is not yet a standard component of routine primary care. Second, even when data is available, many physicians lack the specialized training or the decision-support software necessary to interpret the complex interplay of multiple genetic variants in the context of a patient’s active medication list. Third, the "constellation of variants"—the fact that multiple genes often work in concert to influence drug response—means that simple, single-gene tests are often insufficient.
The Funding Crisis: A Threat to Precision Health
Despite the clear scientific success of the All of Us program, its future is currently clouded by significant fiscal uncertainty. The program has historically relied on two primary funding pillars: the 21st Century Cures Act and annual congressional appropriations. With the Cures Act funding set to conclude in the 2027 fiscal year, the program is bracing for a period of extreme austerity.
Current projections indicate that the program expects to receive approximately $122 million in funding following the finalization of the budget—an 80% decrease from the funding levels enjoyed in 2023. This is not merely a bookkeeping issue; it is having tangible impacts on the program’s ability to function. Joshua Denny, who served as the CEO of All of Us until October 2026, highlighted that the cuts have forced a contraction in community-level engagement. "The engagement activities, the brick-and-mortar that we had enrolling at academic medical centers and FQHCs [Federally Qualified Health Centers] and mobile units—these kinds of things were cut back dramatically," Denny stated.
Perhaps most concerning for the long-term viability of the program is the cessation of the service that provided participants with their own genetic health-related results. Furthermore, the pediatric initiative, which is vital for understanding developmental pharmacology, remains in a state of stasis. Sara Van Driest, director of Pediatrics for All of Us, notes that while approximately 5,000 children have been enrolled, the data is not yet available for research analysis due to the lack of necessary resources to scale the effort.
Equity and the Future of Personalized Care
Loren Saulsberry, a health policy researcher specializing in equity and pharmacogenomics, views the latest findings as a vital step toward reducing health disparities. "This really furthers the emerging evidence of how genetically guided clinical care adds benefit across a diverse population," she explained. However, she warned that the potential for these findings to be translated into equitable clinical care is inextricably linked to the continued health of the research infrastructure.
If the "All of Us" data remains underfunded, the risk is that the benefits of precision medicine will be siloed into affluent medical systems, while the rest of the country remains underserved. The disparity is not just about who gets the drug, but who the drug was designed for. By documenting the unique genetic profiles of diverse populations, the current study has provided a roadmap for inclusive medicine. Whether that map can be followed depends on the willingness of policymakers to prioritize stable, long-term funding for the next generation of precision health research.
As the scientific community digests these findings, the consensus is clear: the data is ready, the clinical value is documented, and the methodology is sound. The bottleneck is no longer in the laboratory, but in the legislative chambers where the future of American medical research funding is decided. Without sustained investment, the promise of precision medicine—a future where every patient receives the right drug at the right dose based on their unique genetic makeup—may remain an elusive goal for the majority of the population.