
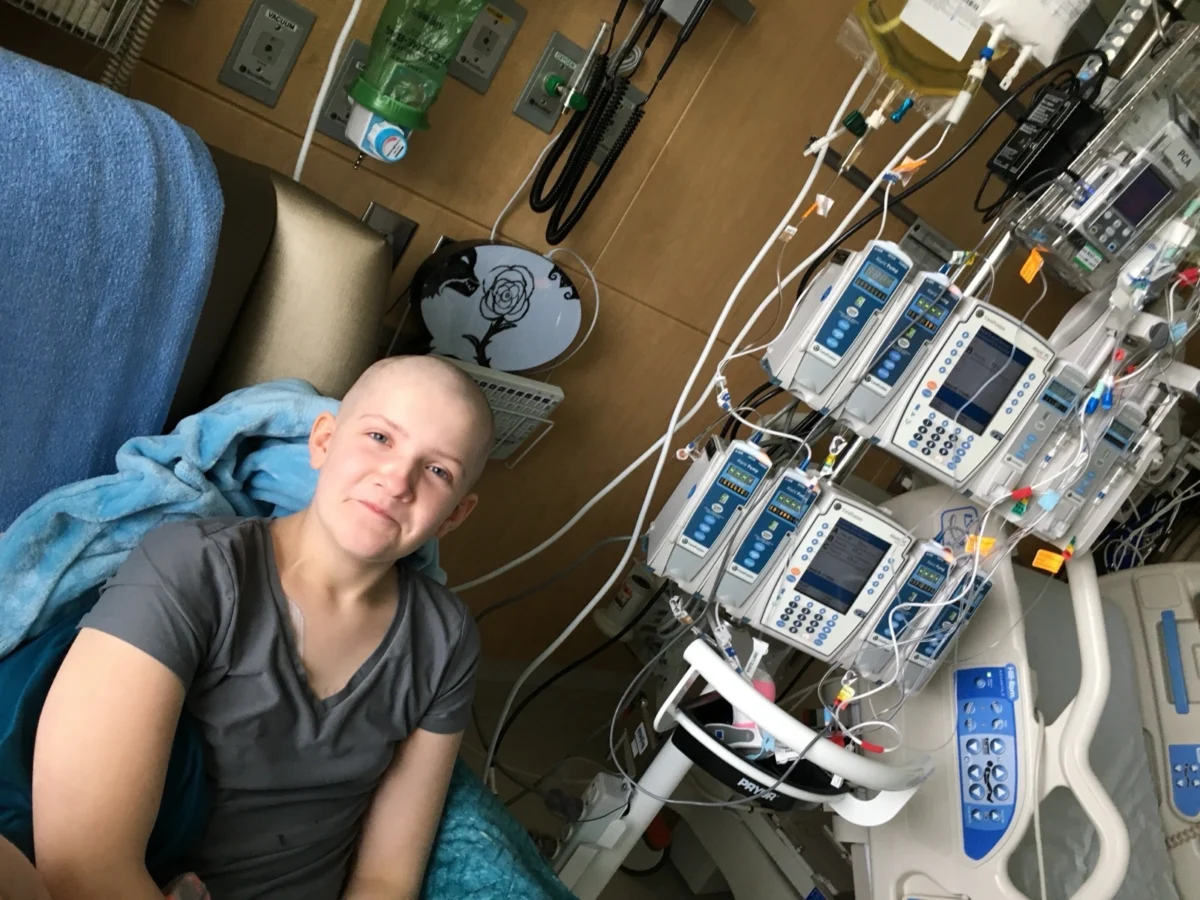
Five years after winning her long and grueling battle against childhood Hodgkin lymphoma, 19-year-old Taya Hailstone finds herself locked in an entirely different kind of fight. Despite enduring severe, lifelong organ and nerve damage that makes foundational, everyday tasks—such as loading a dishwasher, gripping a fork, or walking across a room—a formidable challenge, Hailstone is facing the potential loss of her low-cost disability health coverage. Last year, the Montana Department of Public Health and Human Services abruptly decided she was no longer eligible for Medicaid’s specialized disability healthcare coverage. Instead, officials shifted her status to the state’s Children’s Health Insurance Program (CHIP)—a subsidiary Medicaid program—just three months before she officially aged out of it.
The administrative ruling arrived without the state ever requesting or reviewing the comprehensive medical records compiled by the specialized team of physicians, physical therapists, and counselors treating her. Instead, the decision was triggered after state officials discovered that the teenager had voluntarily stopped receiving her monthly Social Security disability payments. Hailstone had made the difficult decision to pause those payments in a hopeful attempt to achieve health independence, aspiring to work and save money beyond the strict, punitive income caps mandated by those federal funds. However, because her health fluctuates unpredictably day by day—leaving her susceptible to sudden physical crashes, extreme fatigue, severe dehydration from partial intestinal removal, and debilitating swelling in her hands and feet—she remains medically unable to sustain consistent employment.
Today, while her legal team and family formally appeal the state’s decision, Hailstone maintains her Medicaid coverage under appeal status. Without it, the specialized care required to manage the permanent, systemic aftermath of her pediatric cancer treatment would be financially out of reach. Her story highlights a rapidly escalating national crisis. As states across the country begin implementing controversial new federal Medicaid work requirements, legal experts, healthcare advocates, and policy researchers warn that Hailstone’s ordeal is merely a preview of systemic failures that could jeopardize healthcare access for millions of Americans with chronic illnesses and hidden disabilities.
The National Landscape of Medicaid Work Requirements
The structural upheaval facing state-administered Medicaid programs stems from sweeping federal legislation enacted last year. Under the federal framework commonly referred to as the One Big Beautiful Bill Act, Congress established a nationwide mandate requiring states to implement strict work-for-coverage rules by January 2027. Under these new guidelines, an estimated 18.5 million Americans will be forced to routinely prove they are actively working, pursuing education, or participating in approved volunteer activities to maintain their federally subsidized healthcare.
According to data compiled by KFF (formerly the Henry J. Kaiser Family Foundation), more than 40% of these affected enrollees live with chronic health conditions or severe disabilities. While the legislation includes provisions allowing states to excuse individuals who are certified as "medically frail" or too sick to maintain employment, translating these broad statutory exemptions into functional state-level policy has triggered widespread administrative chaos.
Federal agencies subsequently released rules that went significantly beyond the initial scope outlined by Congress, requiring enrollees to not only prove they have a chronic illness, but to explicitly verify that their condition directly prevents them from working. This has forced states to construct complex, resource-intensive medical exemption evaluation systems. Public health advocates argue that these state-level apparatuses are being hastily assembled, are severely underfunded, and risk duplicating or conflicting with the robust, decades-old evaluation protocols maintained by the Social Security Administration (SSA).
A Chronology of Implementation and Legal Pushback
While the federal deadline gives states until early 2027 for total compliance, several jurisdictions have elected to accelerate their rollouts. Nebraska initiated its work requirement checks in May, and Montana followed suit in July, setting an aggressive timeline that has alarmed healthcare advocates and legal aid organizations.
Recognizing the immense administrative hurdles and the high risk of wrongful terminations, a coalition of 25 state attorneys general filed a federal lawsuit against the administration in June, challenging the legality and feasibility of the new medical frailty rules. The plaintiffs argued that the stringent documentation standards are virtually impossible for vulnerable patients to successfully navigate and structurally unmanageable for state agencies to accurately assess. This high-stakes legal challenge remains ongoing in federal court.
Meanwhile, the Congressional Budget Office (CBO) has projected stark figures regarding the policy’s long-term trajectory. By 2034, more than 5 million enrollees are expected to lose their Medicaid coverage entirely due to noncompliance with work verification rules or an inability to successfully navigate bureaucratic exemption processes. Critics note that while the federal government allocated a mere $200 million for states to share in implementing these massive administrative shifts, states are instead funneling tens of millions of dollars into private contractors—such as Deloitte—to overhaul public aid systems that already possess a documented history of processing errors and erroneous coverage denials.
A Closer Look at Taya Hailstone’s Medical and Administrative Journey
For Taya Hailstone, the bureaucratic hurdles feel purposely insurmountable. Diagnosed with blood cancer at the tender age of 10, cancer consumed nearly half of her formative childhood years. Aggressive treatments saved her life, but left her body profoundly altered. Severe tearing in her intestines required partial surgical removal, permanently damaging her digestive system’s ability to process food and leaving her chronically vulnerable to dangerous dehydration. Furthermore, persistent neurological and systemic side effects trigger severe brain fog, intense fatigue, and debilitating swelling in her extremities that frequently compromise her motor skills.

Hailstone and her mother, Kyla Hailstone, reside in Roundup, a small rural community in central Montana with a population of approximately 2,000 residents. Because local medical infrastructure is limited, the family makes a grueling, two-hour round-trip drive to Billings multiple times a week to attend specialized appointments with physical therapists, occupational therapists, and mental health counselors.
The family’s struggle underscores the heavy reliance enrollees must place on navigating labyrinthine bureaucratic systems. Kyla Hailstone notes that the Montana Department of Public Health and Human Services has repeatedly failed to transparently communicate the exact criteria used to strip her daughter of disability status, and has dragged its feet throughout a slow, dysfunctional appeals process.
"It feels like this process was made to make you give up," Taya Hailstone said. "If I lose this, this is life-changing."
Official Responses and Systemic Vulnerabilities
When pressed for comment regarding Hailstone’s specific case, Jon Ebelt, a spokesperson for the Montana Department of Public Health and Human Services, maintained agency policy against commenting on individual Medicaid determinations. However, Ebelt emphasized that the department remains fully committed to treating every client with respect and ensuring that eligible residents receive appropriate coverage. He noted that the state generally honors disability determinations made by the Social Security Administration, and that internal state reviews are only conducted when an individual lacks an active SSA designation, provided they do not qualify for coverage through alternative pathways.
To mitigate the immediate shock of the new rules, Montana instituted a brief three-month grace period, with state officials delaying actual disenrollments for noncompliance until October. Yet, legal experts remain deeply skeptical that a grace period is sufficient to prevent mass coverage losses.
Megan Dishong, deputy director of the Montana Legal Services Association—an organization dedicated to helping low-income residents secure public benefits—expressed deep concern over the state’s institutional capacity. "Whether proper disability evaluations happen is always a bit of a crapshoot just based on state capacity," Dishong explained. "Things fall through the cracks."
Dishong warned that without immediate, transparent structural reforms from state leadership before the October disenrollment deadline, Montana risks creating a "slow-roll mess" that leaves thousands of medically vulnerable residents uninsured. Her concerns are echoed by national policy experts like Pamela Herd, a professor of public policy at the University of Michigan who has extensively studied administrative burdens in social welfare programs.
"When we’ve designed public programs in ways that people can’t figure out whether they’re eligible without consulting lawyers, we’ve done something wrong," Herd observed. "That has huge, huge implications for what’s to come."
The Broader Implications for Patients and Physicians
Beyond the immediate crisis facing individual enrollees, the expanded documentation mandates are placing an unprecedented strain on the broader healthcare ecosystem. Already overburdened physicians and clinical staff express mounting anxiety over being conscripted into administrative roles, forced to act as gatekeepers and judges to determine whether a patient’s medical chart meets rigid, state-defined thresholds for a work exemption.
Critics point out the stark financial and administrative imbalance of the new system. While the federal government spent upwards of $5 billion last year to administer the Social Security Administration’s established disability review system for roughly 7 million Americans, the vastly larger Medicaid population—with tens of millions subject to work checks—is being funneled into a fragmented, underfunded state-level review apparatus.
For Taya Hailstone, the systemic roadblocks have left her with few viable alternatives. Rather than risking the complete loss of her healthcare lifeline, she has begun the arduous process of reapplying for Social Security disability payments. While securing that status will guarantee her continued access to vital Medicaid coverage, it will simultaneously reimpose the rigid income caps that initially discouraged her from attempting to re-enter the workforce, effectively trapping her in a cycle where striving for financial independence jeopardizes her medical survival. As October approaches and states begin enforcing compliance, Hailstone’s battle serves as a stark warning of the human cost exacted when bureaucratic efficiency is prioritized over patient health.










Leave a Reply